Sunday, January 15, 2023

Rank Preserving Structural Failure Time Model (RPSFTM) to account for treatment crossover

In a previous post "Treatment crossover in parallel-group, randomized, controlled clinical trials", treatment crossover was discussed. Treatment crossover (or treatment switching) occurs when patients switch from their randomized arm to the other treatment during the study. In handling the treatment crossover, the naïve approaches (such as ITT analysis, exclusion of the treatment crossover subjects, and censoring at the time of the crossover) can cause a biased estimate of the treatment difference. More sophisticated approaches are needed to handle the treatment crossover. One of these approaches is called 'Rank Preserving Structure Failure Time Model (RPSFTM)". 

RPSFTM method was proposed by Robins and Tsiatis (1991) in their paper "Correcting for Non-Compliance in Randomized Trials Using Rank Preserving Structure Failure Time Models". The RPSFTM is a method used to adjust for treatment switching in trials with survival outcomes. The method is randomization based and uses only the randomized treatment group, observed event times and treatment history in order to estimate a causal treatment effect. The treatment effect is estimated by balancing counter-factual event times (i.e. the time that would be observed if no treatment were received) between treatment groups. 

We are seeing examples of RPSFTM application in oncology trials (especially open-label randomized trials) and in rare disease clinical trials. 

Hussain et al (2022) published a paper on NEJM "Survival with Olaparib in Metastatic Castration-Resistant Prostate Cancer". The results were from an open-label, phase 3 trial where patients were randomly assigned in 2:1 ratio to receive olaparib or physician's choice of enzalutamide or abiraterone plus prednisone as the control therapy. Patients in the control therapy group were allowed to be crossed over to olaparib after imaging-based disease progression criteria were met. Overall survival was analyzed using the naïve approach (intention-to-treat approach). Sensitivity analysis using the RPSFTM method was then performed to adjust for control patient crossover to olaparib.  Kaplan-Meier plots for the observed data and for crossover-adjusted analysis were depicted below: 


EISAI's Lenvatinib was approved for the treatment of patients with progressive, radioiodinerefractory differentiated thyroid cancer. The NDA approval was based on a pivotal study (Study 303). Study 303 is an international, double-blind, randomized 2:1, placebo-controlled, parallel-group, 2-arm trial. Patients would receive lenvatinib or placebo daily and could be treated until disease progression confirmd by IIR (RECIST v1.1) or unacceptable toxicity. The primary endpoint was progression-free survival with secondary endpoints of ORR and overall survival. Patients randomized to the placebo arm who had confirmed progression could choose to cross over and receive open-label lenvatinib. Overall survival was analyzed with the pooled data from the randomized portion of the study and the optional open-label extension phase. The effect of lenvatinib on overall survival was potentially confounded by the crossover of 83% of patients on the placebo arm to receive lenvatinib in the optional open-label (OOL) extension Phase.
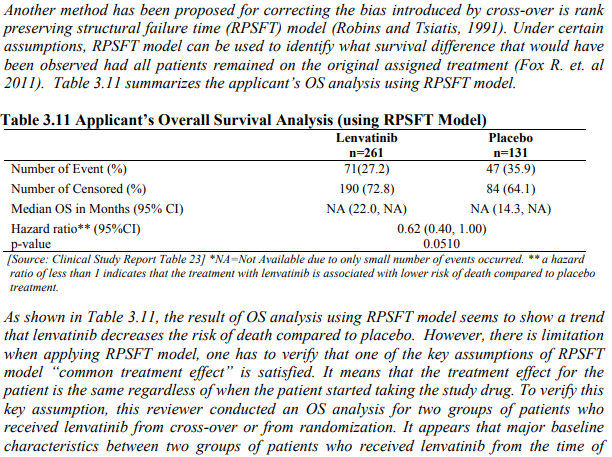
The rank preserving structural failure time (RPSFT) model was then used in OS analysis to correct the bias introduced by cross-over and estimate the true treatment effect on OS. Here is the reference of RPSFT in the FDA's statistical review:


Amylyx's RELYVRIO was approved by FDA for the treatment of ALS. The approval was based on a pivotal study (CENTAUR) and its open-label extension study (CENTAUR-OLE). The pivotal CENTAUR study was a randomized, placebo-controlled, double-blind, 24-weeks study in patients with ALS. Patients who completed 24-week randomized treatment were rolled over to an open-label extension study where all patients received the active drug. Patients in the active drug group in the randomized trial would continue with the active drug in the open-label extension study; patients in the placebo group in the randomized trial would switch or cross over to the active drug. To provide substantial evidence of the effectiveness of the active drug, the sponsor performed the analyses for long-term overall survival with the combined data from the randomized study and the open-label extension study. RPSFTM method was employed to handle the switch or crossover of the placebo patients in the randomized study to active drug in the OLE. Here is the description of the RPSFTM analysis from the briefing book for FDA Adcom. 


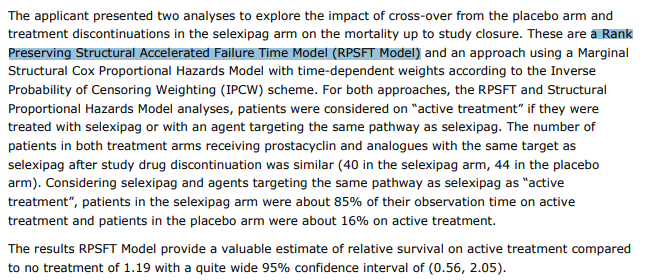
The drug Uptravi was approved for the treatment of pulmonary arterial hypertension. The efficacy and safety were based on a pivotal study followed by an open-label extension study. The pivotal study was designed as an event-driven study where patients who had clinical worsening events would be rolled over to the open-label extension study. The placebo patients in the randomized study would switch or cross over the active drug in the open-label extension study. While the randomized study showed the treatment benefit in reducing the risk of clinical worsening events, there was an imbalance in the number of deaths (more death events in active drug group than the placebo group).  The analyses for long-term overall survival with the combined data from the randomized study and the open-label extension study became necessary to mitigate the concern about the imbalance in the number of deaths observed in the randomized trial. RPSFTM method was employed to handle the switch or crossover of the placebo patients in the randomized study to the active drug in the OLE. EMA's assessment report described the RPSFTM analyses. 

An add-on package (RPSFTM) publically available for fitting rank preserving structural failure time models is available for R (Bond and Allison, 2017), and can be installed from the CRAN web portal. A SAS program was written by Bradford J. Danner and Indrani Sarkarto to perform RPSFTM analysis
 

 Additional References: 

Sunday, January 08, 2023

Treatment crossover in parallel-group, randomized, controlled clinical trials

Randomized, controlled clinical trial (RCT) is the golden standard in drug development. RCTs are usually designed as parallel-group to compare the experimental treatment with a control group (usually the placebo). Eligible patients are randomized to one of the treatment arms (the experimental treatment or placebo). The patients who are randomized to the experimental treatment arm will receive the experimental treatment for the duration of the study and patients who are randomized to the placebo arm will receive the placebo for the duration of the study. 

There are situations where the treatment crossover is allowed by the protocol and the treatment crossover is usually one-sided (i.e., patients on the placebo arm crossed over to the experimental treatment arm, not patients on the experimental treatment arm crossed over to the placebo arm). Treatment crossover can be seen in oncology clinical trials (especially the open-label, randomized trials) or in rare disease clinical trials where the RCT is followed by an open-label extension study. 

In EMA's scientific guidance "Question and answer on adjustment for cross-over in estimating effects in oncology trials", the treatment crossover was described as the following:

In oncology trials, one-sided cross-over of control patients to the experimental treatment may occur, e.g. after progression. No objections from a methodological perspective exist against systematic crossover, where systematic means that there is an objective criterion which determines whether a control patient will cross over to the experimental treatment, or not. One example is when all control patients switch to experimental treatment at the same calendar time (e.g. after an interim analysis declaring superiority); however, this is provided that unconfounded overall survival (OS) data are not considered necessary to evaluate efficacy or safety. Another example of systematic cross-over is when by design a control patient must switch to experimental treatment when that patient experiences progression and the outcome is another measure than progression, e.g. OS, if it is justified to use this design. Nonsystematic cross-over can occur, for instance, when the study protocol allows cross-over after progression at the discretion of the investigator. This document addresses the situation where crossover of control patients is not systematic and there is interest in estimating the effect in the (hypothetical) situation that no cross-over would have occurred in the trial, under the assumption that the experimental treatment cannot introduce harm or deterioration of the condition under investigation in the control patients who cross over. In particular, it should be fully justified that this hypothetical effect is a relevant one for regulatory decision making. It should be noted that due to the uncertainties involved in the methods described below, such estimations should, at present, be used primarily as supportive or sensitivity analyses. 

The guidance defines the treatment crossover as systematic crossover and nonsystematic crossover:

  • Systematic crossover is for clinical trials where there is an objective criterion which determines whether a control patient will cross over to the experimental treatment, or not
  • Nonsystematic cross-over can occur, for instance, when the study protocol allows cross-over after progression at the discretion of the investigator

Systematic crossover can be seen in the following situations: 

  • all control patients switch to experimental treatment at the same calendar time (e.g. after an interim analysis declaring superiority; at the time of study closure)
  • individual patients switch to experimental treatment at a different time when patient experiences an event (progression, clinical worsening event, or complete the scheduled treatment duration)
  • or a mixture of both situations above
In rare disease areas, the clinical development program usually includes an RCT followed by an open-label study. Because of the rarity of the patients and lack of alternative treatment options, clinical trial participants who complete the randomized portion of the study will be rolled over to an open-label extension (OLE) study where all patients receive experimental treatment. To consider the RCT portion and OLE portion of the study as a whole, the patients in the control arm are crossed over to the experimental treatment arm and the patients in the experimental treatment arm continue the experimental treatment (no crossover). By design, patients who receive the control in the RCT portion of the study cross over to experimental treatment in the OLE portion of the study, which is a perfect example of a systematic crossover. 

Amylyx conducted a phase 2 RCT with a fixed treatment duration (24 weeks) "Trial of Sodium Phenylbutyrate–Taurursodiol for Amyotrophic Lateral Sclerosis". Patients who completed 24 weeks of study treatment (Sodium Phenylbutyrate–Taurursodiol or placebo) were then rolled over a separate open-label extension study where all patients received Sodium Phenylbutyrate–Taurursodiol. Overall survival was analyzed using the combined data from both the RCT and the OLE studies. This can also be viewed as a one-sided crossover where all patients in the placebo arm crossed over to the experimental treatment arm in the OLE. In this case, individual patients switch to experimental treatment at different calendar times, but all after the scheduled RCT duration of 24 weeks. 

The RCT could also be designed as an event-driven study, patients who experienced an event would then be rolled over to the OLE study. Patients who do not experience an event would also be rolled over the OLE study at the RCT study closure when the total number of events was reached. This situation can also be viewed as a one-sided crossover where all patients in the placebo arm crossed over to the experimental treatment arm when they are rolled over to the OLE study. In this case, individual patients who experience an event switch to experimental treatment at different calendar times, but individual patients who do not experience an event switch to experimental treatment at the same calendar time after the total number of events are reached and the study is closed.  See the following examples: 

Different approaches can be employed to analyze the data from clinical trials with one-sided treatment crossover. 

EMA's scientific guidance "Question and answer on adjustment for cross-over in estimating effects in oncology trials" mentioned the following methods:

Different statistical methods have been proposed to adjust overall survival for cross-over, including analysis censoring at time of cross-over, Inverse Probability of Censoring Weighting (IPCW), Rank Preserving Structural Failure Time models (RPSFT), and ‘two-stage’ methods.

In principle, these methods can (be adapted to) address different questions by formulating distinct estimands. For example, IPCW estimates the effect of the experimental treatment versus control as if cross-over by control group patients to the experimental treatment was absent but still includes subsequent therapies. Using RPSFT the analyst could choose the estimate to aim at the effect of experimental therapy only (effect of being ‘on experimental treatment’), but in practice the effect of experimental therapy and subsequent therapies (effect of ‘ever being treated’) is often estimated.

In a presentation by Norbert Hollaender "Methods to estimate survival time after treatment switching in oncology– overview and practical considerations", the following simple('naive') methods and complex methods were discussed:

Simple (‘naive’) methods 

    • Intent to treat analysis: as randomized and ignoring that some patients switched
    • Exclude treatment switchers: small sample size for control group; destroying the randomization; may produce biased results
    • Censor switches at time of ‘cross-over’: informative censoring -> results may be biased
    • Time-varying treatment variable: No longer a comparison between randomized Treatment vs. Control arm, more difficult interpretation

Complex methods 

    • Inverse-probability-of-censoring weighting (IPCW) :
      • Switchers are censored at ‘time point of cross-over’, but patients are weighted according to their probability to switch treatment.
      • IPCW method artifically increases weights for patients with low probability of treatment switch and decreases weights for patients with high probability of treatment switch
    • Rank Preserving Structural Failure Time (RPSFT) Model
      • The RPSFTM models the counter-factual or treatment-free event time
      • Estimate the survival time gained/lost by receiving active treatment

In practice, for clinical trial data containing patients with one-sided treatment crossover, the overall survival data may be analyzed using both RPSFT and IPCW methods. The results from different methods can then be compared. For example, in EMA's assessment report for Uptravi (selexipag), both RPSFT and IPCW methods were used to evaluate overall survival with the data from the RCT and the OLE studies. 

The applicant presented two analyses to explore the impact of cross-over from the placebo arm and treatment discontinuations in the selexipag arm on the mortality up to study closure. These are a Rank Preserving Structural Accelerated Failure Time Model (RPSFT Model) and an approach using a Marginal Structural Cox Proportional Hazards Model with time-dependent weights according to the Inverse Probability of Censoring Weighting (IPCW) scheme. For both approaches, the RPSFT and Structural Proportional Hazards Model analyses, patients were considered on “active treatment” if they were treated with selexipag or with an agent targeting the same pathway as selexipag. The number of patients in both treatment arms receiving prostacyclin and analogues with the same target as selexipag after study drug discontinuation was similar (40 in the selexipag arm, 44 in the placebo arm). Considering selexipag and agents targeting the same pathway as selexipag as “active treatment”, patients in the selexipag arm were about 85% of their observation time on active treatment and patients in the placebo arm were about 16% on active treatment.

The results RPSFT Model provide a valuable estimate of relative survival on active treatment compared to no treatment of 1.19 with a quite wide 95% confidence interval of (0.56, 2.05).

Using the Structural Proportional Hazards Model with IPCW weighting the estimate for the hazard ratio for death as if all patients had received active treatment compared to the situation if all patients had never received active treatment was 0.92 with a 95% confidence interval of (0.58, 1.47) for the 1 month time intervals, showing a slight advantage for treatment with selexipag. Both estimations with models with longer time intervals show non-significant lower hazard ratios (0.79 and 0.75).

Friday, December 23, 2022

Assessing potential unblinding due to imbalance in side effects through exit questionnaires

The critical features of the RCTs include '(concurrent) control', 'randomization', and 'blinding'. These clinical trial features can minimize the conscious or unconscious biases in the endpoint assessments including both the efficacy and safety assessments.
 
Blinding is a procedure in which one or more parties in a trial are kept unaware of which treatment arms participants have been assigned to, i.e. which treatment was received. On the contrary, unblinding is the process by which the treatment allocation is broken so that one or more parties in a trial become aware of the treatment arms the trial participants are on. To maintain the integrity of the RCT trial, the unblinding should occur only after the completion of the study and after the clinical database has been locked (no further modifications to the clinical data) or only in some special situations (unblinding for data monitoring committee, unblinding of the individual trial participants for SUSAR reporting,...). A couple of previous posts discussed exactly the same issue. 

Blinding is an important aspect of any trial. How a trial was blinded should be accurately recorded in order to allow readers to interpret the results of a study. If blinding is ever broken during a trial on individual participants, it needs to be justified and explained.

To implement and maintain the blinding (or treatment concealment), the clinical trial materials need to be manufactured and packaged in the same way. The control group (typically placebo) will have the same specifications as the testing product in shape, size, color texture, weight, taste, and smell. 

The most difficult part of maintaining the blinding is that the testing product and the control product (usually placebo) may have different side effects. The clinical trial participants and the investigators may be able to guess which treatment group the participants are on. It is quite challenging to defend the integrity of the blinding if two treatment groups do have different side effects or adverse event profiles. 

Amylyx recently ran into this issue and successfully defended the integrity of the blinding for their pivotal study (CENTAUR trial) that was published in NEJM. CENTAUR trial results were the basis for Amylyx's NDA submission. In a rare occurrence, FDA organized two external committee meetings by the Peripheral and Central Nervous System Drugs Advisory Committee (PCNS). 

In the first PCNS adcom meeting on March 30, 2022, the integrity of maintaining the blinding was raised:
"The potential for diarrhea and bitter taste were described in the informed consent, which may have alerted the patients to these symptoms and could have led to functional unblinding during the study. These are potential review issues we have identified which contribute to the uncertainty of the results."
In the second PCNS adcom meeting on September 7, 2022, the sponsor addressed the potential unblinding issue in their briefing book:


The sponsor concluded:
"Based on an exit questionnaire performed at the end of the randomized phase, it asked investigators and participants what treatment arm they were assigned to. Neither study investigators nor participants were able to guess the treatment assignment. The active group was not able to guess their treatment assignment any better than chance, indicating that taste and GI adverse events were not leading to unblinding."
Assessing the blinding through exit questionnaires can be risky though. As described in my previous post "Is blinded study really blinded? - assessment of blinding /unblinding in clinical trials":
"Ideally, in a double-blind trial, it is a good practice to evaluate for both the subjects and investigators whether or not blinding / masking has been preserved. However, in the real world, it is rare in double-blinded clinical trials to include a formal assessment of how well the blinding has been preserved. If the assessment of blinding becomes a routine, I think that many studies will show that subjects/investigators guessed correctly more frequently than they should have done by chance alone. Part of the reason this assessment has not been done often is perhaps the difficulty to explain the study results if the blinding is found to be compromised. It will be extremely difficult to assess the magnitude of the impact on the safety and efficacy evaluation if the blinding/treatment assignment concealment is compromised."

Thursday, December 01, 2022

Sample size re-estimation or sample size increase?

Recently, a press release from a biotech company caught my eye. This seems to be an example of the adaptive design with sample size re-estimation, however, it is unusual that the sample size is decreased as usually the sample size re-estimation results in an increase in sample size. 
Bellerophon Therapeutics, Inc. (Nasdaq: BLPH) (“Bellerophon” or the “Company”), a clinical-stage biotherapeutics company focused on developing treatments for cardiopulmonary diseases, announced today that the U.S. Food and Drug Administration (FDA) has accepted the Company’s proposal to reduce the study size for its ongoing registrational REBUILD Phase 3 trial of INOpulse® for the treatment of fibrotic Interstitial Lung Disease (fILD). The new study size of 140 subjects does not impact the trial’s principal objective or endpoints and maintains power of >90% (p-value < 0.01) for the primary endpoint of Moderate to Vigorous Physical Activity (MVPA) based on the effect size observed in Phase 2.

Following the evaluation of baseline MVPA characteristics, as measured by actigraphy, compliance to treatment and review of safety data of the randomized subjects in the ongoing Phase 3 REBUILD study, the trial’s independent Data Monitoring Committee (DMC) supported reducing the target study size from 300 to 140 subjects.
Sample size re-estimation is one type of adaptive design where the sample size can be adjusted during the study based on a prespecified rule. Sample size re-estimation has its special features:  

Group Sequential Design (GSD) and Sample Size Re-estimation

Clinical trials with adaptive design can be in different forms depending on what the adaptations are. Two commonly utilized adaptive designs are group sequential design (GSD) and sample size re-estimation (SSR). Implementation of both GSD and SSR is through the interim analyses conducted by the independent data monitoring committee. In GSD studies, we set a large sample size and hope to stop the trial early due to the overwhelming efficacy, futility, or safety at the interim analyses. In adaptive design with SSR, we start with a small study and possibly increase the sample size post an interim analysis. Both GSD and SSR can achieve the same benefits of reduced sample size and potentially an earlier conclusion. 

Blinded Sample Size Re-estimation and Unblinded Sample Size Re-estimation

In FDA guidance "Adaptive Designs for Clinical Trials of Drugs and Biologics", sample size re-estimation was described in section B "adaptations to the sample size". Blinded sample size re-estimation is based on interim estimates of nuisance parameters such as the standard deviation for continuous outcome measure and overall event rate for discreet outcome measure. The unblinded sample size re-estimation is a type of adaptive design where adaptation is to prospectively plan modifications to the sample size based on comparative interim results. Blinded sample size re-estimation may be conducted by the sponsor statistician while unblinded sample size re-estimation must be through an independent data monitoring committee.  

Sample Size Re-estimation and Sample Size Increase

In clinical trials with prospectively planned sample size re-estimation, the sample size is usually increased. It is very rare that the sample size is decreased after the interim analysis. For adaptive clinical trials with adaptation on sample size (i.e., sample size re-estimation), the initial sample size estimation can be based on more aggressive assumptions that result in a smaller sample size. In the middle of the study, interim analyses are performed and the decision can be made (by independent DMC and through a prespecified rule) whether or not the sample size should be increased. 

In FDA's guidance discussing the Adaptations to Sample Sizes, while the terms 'sample size re-estimation' and 'sample size adaptation' are used, the sample size increase is really implied. 

Sample Size Adaptation and Sample Size Increase by a Fixed Number

The sample size re-estimation or sample size adaptation is really a binary decision. If the decision is to increase the sample size (after the interim analysis), the sample size will be increased by a pre-specified, fixed number, not increased by a number that is based on the observed treatment effect at the interim analysis. 

If the sample size is increased by a very exact level calculated from the observed treatment effect at the interim analysis to bring the conditional power up to a target level, there is a potential to reverse calculate the effect size or to at least make an educated guess about what the effect size is from the interim analysis

This potential for an educated guess about the effect size is a huge issue from the regulatory point of view. This specific concern is discussed in FDA's guidance ""Adaptive Designs for Clinical Trials of Drugs and Biologics".

Finally, there are additional challenges in maintaining trial integrity in the presence of sample size adaptations. For example, sample size modification rules are often based on maintaining the conditional probability of a statistically significant treatment effect at the end of the trial (often called the conditional power) at or near some desired level. In this scenario, knowledge of the adaptation rule and the adaptively chosen sample size allows a relatively straightforward back-calculation of the interim estimate of treatment effect. Therefore, additional steps should be taken to limit personnel with this detailed knowledge so that trial integrity can be maintained.

Tuesday, November 29, 2022

Randomized withdrawal design in action - Accord trial in Alzheimer's agitation

The biotech company, Axsome Therapeutics, announced the positive results from one of their pivotal phase 3 studies (Accord study). 

Axsome's approved depression drug clears Alzheimer's agitation trial months after Lundbeck-Otsuka duo

The unique side of the Accord study is the use of a randomized withdrawal design. The study was registered on clinicaltrials.gov as "A Double-blind, Placebo-controlled, Randomized Withdrawal Trial to Assess the Efficacy and Safety of AXS-05 for the Treatment of Agitation in Subjects With Dementia of the Alzheimer's Type"

With the randomized withdrawal design, all participants were given the active drug (AXS-05) in a run-in phase in an open-label manner. Then, those patients who responded to treatment during the run-in phase were randomly assigned, in a double-blind manner, to either continue treatment with AXS-05 or switch to a placebo.

According to the sponsor, the basic idea behind this randomized withdrawal study design is to see whether those who initially experience a benefit stop doing so when moved to a placebo, indicating that the therapy itself is effective — as opposed to results being due to a placebo effect. The randomized-withdrawal design of this phase 3 trial simultaneously improved signal detection and mitigated placebo response. 

With the randomized withdrawal design, the sample size was reduced. Total 178 patients with Alzheimer's disease agitation were enrolled into the study run-in phase. 108 patients who achieved a sustained clinical response were then included in the randomized withdrawal period. 
"The ACCORD study was a double-blind, placebo-controlled, multi-center, randomized withdrawal, U.S. trial which treated 178 patients with Alzheimer’s disease agitation. Patients achieving a sustained clinical response after open-label treatment with AXS-05 were randomized (n=108) in a 1:1 ratio to continue treatment with AXS-05 or to discontinue AXS-05 and switch to placebo."
According to an article on evaluate.com:

"When Axsome decided to stop the Accord study of AXS-05 in Alzheimer’s disease agitation early, hopes for that trial took a nosedive. So it was clearly a pleasant surprise today when the company announced that the study had hit. Axsome’s stock opened up 33%, and some investors might be hoping for an earlier-than-expected filing, despite the fact that results from the pivotal Advance-2 study are not due until 2025. Accord had initially been intended as a second pivotal, alongside the previously completed Advance-1, but when the number of agitation events turned out lower than expected, management decided to switch focus to Advance-2. Despite this, Accord met its primary endpoint, time to relapse of agitation, and a key secondary, relapse prevention. One potential fly in the ointment could be Accord’s randomised withdrawal design; it comprised an open-label lead-in phase in which all 178 patients were given AXS-05, and those that had a sustained clinical response to the agent were randomised to either continue treatment or switch to placebo. AXS-05, a combination of dextromethorphan and bupropion, is approved in depression as Auvelity and moving into Alzheimer’s agitation would be an important expansion."

Given that Alzheimer's agitation is a common disease (70% of Alzheimer's disease patients may have agitation), more than one adequate and well-controlled study (or pivotal, confirmatory studies) are needed to demonstrate substantial evidence for effectiveness. Besides the Accord study (with randomized withdrawal design), two additional studies were conducted by the sponsor: ADVANCE-1 trial was a Phase 2/3 study with an active control arm. ADVANCE-2 trial is a phase 3 confirmatory study with the largest sample size (350 patients in a 1:1 randomization ratio). ADVANCE-1 study results had already been announced. ADVANCE-2 study has just started the enrollment. Both ADVANCE-1 and ADVANCE-2 studies were designed as traditional RCT design - randomized, double-blind, placebo-controlled, parallel groups. 

In a clinical program containing multiple pivotal clinical trials, it is appropriate to select different clinical trial designs. In Axsome's Alzheimer's agitation clinical program, a randomized withdrawal design was used in one of the three pivotal trials, and a traditional RCT design was used in the other two pivotal trials. If all these three trials are successful, the evidence for effectiveness will be more substantial and stronger than three studies with the same study design. 

Tuesday, November 15, 2022

Treatment Emergent AEs (TEAEs), On-Study AEs, On-Treatment AEs, Non-TEAEs

During the clinical trial, the adverse events (AEs) are collected from the signing of the informed consent to the last dose of the study drug plus some follow-time. For statistical analyses of adverse event data, the treatment-emergent AEs (TEAEs) are usually defined. AEs with an onset date at or after the first dose of the study drug will be defined as TEAEs. AEs with an onset date prior to the first dose of the study drug will then be defined as Non-TEAEs. 

For example, the TEAE can be defined as:

"TEAEs are defined as events that start within the day of the first dose of trial treatment until 28 days after the last dose of treatment" in an SAP for an EMD Serono study.

"Treatment-emergent AEs (TEAEs) are defined as AEs that are not present at baseline or represent an exacerbation of a preexisting condition during the treatment period. Therefore, referencing the protocol, TEAEs will be defined programmatically as any AE record with a start date/time on or after the first study treatment administration (greater than or equal to study day 1), inclusive to the end of the study (specifically the EOS visit or ET visit)." in an SAP for a Regeneron's study

The TEAEs can be further defined based on the comparison of the AE onset date with a cut-off date where the cut-off date may be the last dose date or 28 days after the last dose date. 

In FDA's clinical review document for AstraZeneca's asthma drug, the on-study AE and on-treatment AE were defined:

  • On-study AE: events with onset between the first-day dosing and the scheduled follow-up visit. 
  • On-treatment AE: events with onset between the first day of treatment and the scheduled end of treatment (EOT) or investigational product discontinuation (IPD) visit. 
  • Post-treatment AE: events with onset after the on-treatment period defined above

 On-study AEs include all TEAEs - all AEs recorded on or after the first dose date. 

On-treatment AEs are a subset of all TEAEs or on-study AEs. The AEs with an onset date after the cut-off date will be excluded from on-treatment AEs. 

There are some clinical trials with on-treatment AEs defined as the same as traditional TEAEs (i.e., any AEs with an onset date on or after the first dose of the study drug regardless of the cut-off date).

In a recent workshop "Advancing Premarket Safety Analysis" organized by FDA and Duke Margolis Center for Health Policy, the on-study and on-treatment AEs were specifically discussed. Here are the presentation slides for this topic:


The concept of on-treatment AEs has already been implemented in some clinical trials. For example, in a GSK-sponsored trial "A Phase 3a, Repeat Dose, Open-label, Long-term Safety Study of Mepolizumab in Asthmatic Subjects", the primary outcome measure is "Number of Participants With Any On-treatment Adverse Event (AE) or On-treatment Serious AE (SAE)" where On-treatment AEs and on-treatment SAEs are the events occurring on/after the first dose of open-label mepolizumab date and before/on last dose+28 days.

In a BMS trial "A randomized, open-label, phase 3 study of  BMS-936558 vs. Everolimus in Subjects with advanced or metastatic clear-cell renal cell carcinoma who have received prior anti-angiogenic therapy", the on-treatment AEs were defined as the following with a cut-off date of 100 days of the last dose of study treatment.
"On-treatment AEs will be defined as AEs with an onset date-time on or after the DateTime of the first dose of study treatment (or with an onset date on or after the day of first dose of study treatment if time is not collected or is missing). For subjects who are off study treatment, AEs will be counted as on-treatment if event occurred within 100 days of the last dose of study treatment. No “subtracting rule” will be applied when an AE occurs both pre-treatment and post-treatment with the same preferred term and grade."
Defining on-treatment AEs will require specifying a cut-off date and the cut-off date may be different depending on the potential impact of the study drug after the drug discontinuation and the half-life of the investigational products. 

Defining on-treatment AEs may be necessary for studies with the treatment policy estimand where the efficacy data and AE/SAEs are continued to be collected after the study participants have discontinued the study treatment. 

Previous discussions: 

Friday, November 11, 2022

Rolling Review, Real time oncology review (RTOR), and Split real time application review (STAR) Program

For New Drug Application (NDA) and Biological License Application (BLA), the usual process is to submit the entire package with different modules at the same time. The submission package will include the quality, CMC, non-clinical study reports, and clinical study reports,... However, there are processes by which the sponsor can submit the submission package piece by piece: rolling review, real-time oncology review, and split real-time application review (STAR) program.

Rolling Review

Rolling review was one of the benefits for drug products with Fast Track Designation. According to FDA's website "Fast Track" 
A drug that receives Fast Track designation is eligible for some or all of the following:

More frequent meetings with the  FDA to discuss the drug's development plan and ensure the collection of appropriate data needed to support drug approval

More frequent written communication from FDA about such things as the design of the proposed clinical trials and use of biomarkers

Eligibility for Accelerated Approval and Priority Review, if relevant criteria are met

Rolling Review, which means that a drug company can submit completed sections of its Biologic License Application (BLA) or New Drug Application (NDA) for review by FDA, rather than waiting until every section of the NDA is completed before the entire application can be reviewed. BLA or NDA review usually does not begin until the drug company has submitted the entire application to the FDA
Fast Track Designation was one of the expedited programs described in FDA's guidance "Expedited Programs for Serious Conditions – Drugs and Biologics". Other expedited programs are breakthrough therapy designation, accelerated approval, and priority review designation. In FDA's guidance, the Fast Track Designation contains the benefit of submission of portions of an application (Rolling Review): 


Here are rolling review examples: earlier this month, Iveric Bio Announces Submission of First Part of NDA for Rolling Review of Avacincaptad Pegol for the Treatment of Geographic Atrophy; in September, 2022, Vertex and CRISPR Therapeutics Announce Global exa-cel Regulatory Submissions for Sickle Cell Disease and Beta Thalassemia

Real-Time Oncology Review (RTOR) Program

For oncology products, FDA's The Oncology Center of Excellence has a program called "real-time oncology review (RTOR)". RTOR facilitates earlier submission of topline efficacy and safety results, prior to the submission of the complete application, to support an earlier start to the FDA’s evaluation of the application. FDA's website "Real-Time Oncology Review" described the details about RTOR program. 

Some companies have utilized this program in hope of expediting their submission/review process. 
In a press release "SpringWorks Therapeutics Announces Data from Phase 3 DeFi Trial Evaluating Nirogacestat in Adult Patients with Progressing Desmoid Tumors at the European Society for Medical Oncology (ESMO) Congress 2022", it stated that their Nirogacestat for R/R desmoid tumors will be filed through real-time oncology review (RTOR) program.
Nirogacestat has received Orphan Drug Designation from the U.S. Food and Drug Administration (FDA) for the treatment of desmoid tumors and from the European Commission for the treatment of soft tissue sarcoma. The FDA also granted Fast Track and Breakthrough Therapy Designations for the treatment of adult patients with progressive, unresectable, recurrent or refractory desmoid tumors or deep fibromatosis. SpringWorks plans to submit a New Drug Application (NDA) to the FDA in the second half of 2022, which will be submitted for review under the FDA’s Real-Time Oncology Review (RTOR) program.

Amgen's Sotorasib was approved by FDA for the first and only targeted treatment for patients with KRAS G12C-mutated locally advanced or metastatic non-small cell lung cancer. The Sotorasib's BLA submission was through RTOR:

"In the U.S., LUMAKRAS was reviewed by the FDA under its Real-Time Oncology Review (RTOR), a pilot program that aims to explore a more efficient review process that ensures safe and effective treatments are made available to patients as early as possible."

 An article in Life Science Leader magazine "FDA's RTOR Program: Draft Guidance & Insights" provides a good summary of the RTOR program.

Split Real-Time Application Review (STAR)

STAR program builds off the Oncology Center of Excellence’s Real-Time Oncology Review (RTOR) program, In the newly passed PDUFA VII for the years 2023 through 2027, a new program called Split real-time application review (STAR) was proposed. According to PDUFA reauthorization performance goal and procedures fiscal years 2023 through 2027, the STAR program was described as the following: 
D. SPLIT REAL TIME APPLICATION REVIEW (STAR) PILOT PROGRAM
FDA will establish a STAR pilot program, which has the goal of shortening the time from the date of complete submission to the action date, in order to allow earlier patient access to therapies that address an unmet medical need. The STAR pilot program will apply to efficacy supplements across all therapeutic areas and review disciplines that meet specific criteria. Accepted STAR applications will be submitted in a “split” fashion, specifically in two parts (with the components submitted approximately 2 months apart).

1. Scope: The STAR program will seek to expedite patient access to novel uses for existing therapies by supporting initiation of review earlier than would otherwise occur and therefore allowing earlier approval for qualified efficacy supplements. This program will apply across all therapeutic areas and review disciplines for applications that meet specific criteria. An application will be considered eligible for STAR if each of the following criteria are met: a. Clinical evidence from adequate and well-controlled investigation(s) indicates that the drug may demonstrate substantial improvement on a clinically relevant endpoint(s) over available therapies. Breakthrough Therapy Designation (BTD) or Regenerative Medicine Advanced Therapy Designation (RMAT) is not required, but above criteria must be met. b. The application is for a drug intended to treat a serious condition with an unmet medical need. c. No aspect of the submission is likely to require a longer review time (e.g., requirement for new REMS, etc.). d. There is no chemistry, manufacturing, or control information that would require a foreign manufacturing site inspection (i.e., domestic site inspections may be allowed if it does not affect the expedited timeframe).
FDA's website "Split Real-Time Application Review (STAR)" described how the STAR program should be operated.

Thursday, October 20, 2022

Multiple Endpoints in Clinical Trials (Final) - FDA Guidance for Industry

Today, the FDA finalized its guidance for industry "Multiple Endpoints in Clinical Trials". The draft version of this guidance was issued in 2017. The guidance is intended to help sponsors better understand FDA's current thinking about the issues related to the multiple endpoints and multiplicity issues for multiple endpoints, and different approaches in handling multiplicity issues. The guidance also discussed composite endpoints and multi-component endpoints. 

Typically, an adequate and well-controlled study will include only one primary efficacy endpoint and then multiple secondary efficacy endpoints, and additional exploratory endpoints. Exploratory endpoints are those endpoints for research purposes or for new hypotheses generation and not for the purpose of the product label. Primary and secondary efficacy endpoints can potentially be included on the product label. However, the testing hierarchy and sound approach for multiplicity adjustment must be pre-specified. The Fixed-Sequence Method in the appendix of this guidance seems to be commonly used. With Fixed-Sequence Method, the secondary efficacy endpoints will be tested only if the primary efficacy endpoint is statistically significant. The secondary efficacy endpoints are ranked or ordered based on the importance of the endpoints and the likelihood of getting statistically significant results. The next secondary efficacy endpoint will be tested only if the previous secondary endpoint is statistically significant. The testing hierarchy will stop once the hypothesis test for one of the secondary endpoints is not statistically significant.  

If the sponsor wants to include secondary endpoints in the product label, multiplicity adjustment for secondary endpoints must be included in the statistical analysis plan. 

In the section discussing the co-primary endpoints, "When Demonstration of Treatment Effects on Two or More Distinct Endpoints Is Recommended to Establish Clinical Benefit (Co-Primary Endpoints)", the examples of clinical trials with co-primary endpoints included in the draft version of this guidance were removed from the final guidance. For example, the draft guidance mentioned the following example and the final guidance did not:


Presumably, this is due to the revised FDA guidance "Early Alzheimer's Disease: Developing Drugs for Treatment" and the availability of the integrated scale - Clinical Dementia Rating Sum of Boxes (CDR-SB) Score:

"An integrated scale that adequately and meaningfully assesses both daily function and cognitive effects in early AD patients is acceptable as a single primary efficacy outcome measure. " 

"Common Statistical Methods for Addressing Multiple Endpoint-Related Multiplicity Problems" was included in the body of the guidance in the draft guidance and is now moved to the Appendix: Statistical Methods. The list of methods remains the same and includes the Bonferroni method; the Holm procedure; the Hochberg procedure; prospective alpha allocation scheme; the fixed-sequence method; resampling-based, multiple-testing procedures; gatekeeping testing strategies; and graphical approaches based on sequentially rejective tests. 

As a regulatory agency, FDA is conservative and tries to avoid false conclusions. Without adequate adjustment for multiplicity, the alpha level (type I error rate) can be inflated, and statistically, significant differences may be wrongly declared for an ineffective drug. In the summary of this guidance, FDA concludes: 

Previous Posts:

Sunday, October 16, 2022

Risk difference and confidence interval for Analyses of AEs and Clinical Laboratory Data

Several years ago, I posted an article "Should hypothesis tests be performed and p-values be provided for safety variables in efficacy evaluation clinical trials?". There are some new development on this topic. 

Recently, FDA in collaboration with the Duke-Margolis Center for Health Policy hosted a one-day virtual meeting focused on advancing pre-market safety analytics. At this workshop, it was revealed that FDA Biomedical Informatics and Regulatory Review Science (BIRRS) Team was working on a document called "Standard Safety Tables and Figures: Integrated Guide". The document is currently posted on regulations.gov for public comments. The integrated guide proposed the mockup shells how the safety data analyses (adverse events and clinical laboratory data) should be displayed. Throughout all the proposed shells, we can see that a column for "'Risk Difference (%) (95% CI)" are included. Here are a couple of examples. 


If this integrated guide become official and is implemented, the future analyses for safety data (adverse events and clinical laboratory parameters) will be shifted from the pure summary statistics to summary statistics + point estimate and 95% confidence interval for risk differences. p-values and hypothesis testing should not be provided. 

Risk difference and its 95% confidence interval are provided for the descriptive purpose, not for inferential purpose. As stated in the integrated guide "These safety analyses are exploratory in nature and confidence intervals (CIs) for the risk difference presented here are not adjusted for multiplicity."

In AE tables, the sort order will be by the risk difference (from the highest to the lowest). In this way, the reviewers can easily identify the AEs with largest risk difference between two treatment groups. 

There are several ways in calculating the confidence interval for risk difference. The commonly used approach is Wilson score method - a method of estimating the population probability from a sample probability when the probability follows the binomial distribution.

There seems to be some differences between the regulatory requirement and the requirement by the medical journals. We continue to see the requests from journals like New England Journal of Medicine for providing the p-values for AE summary tables. In our published article, "Inhaled Treprostinil in Pulmonary Hypertension Due to Interstitial Lung Disease", we had to provide the p values for AEs and other safety endpoints for treatment group comparison per NEJM's editor's request. 

Saturday, October 08, 2022

PDUFA, GDUFA, BSUFA, and MDUFA - FDA's User Fee Programs

For professionals who are working in drug development areas, the term PDUFA should be a very familiar term. As a matter of fact, FDA's action date or decision date to approve a new drug application (NDA) or biological license application (BLA) is called 'PDUFA date'. There are several trackers to track FDA's calendar for NDA/BLA approvals based on the PSUFA dates. 

PDUFA stands for 'Prescription Drug User Fee Amendments' and it is a program allowing FDA to collect the application fees from the sponsor. The PDUFA was created by Congress in 1992 and authorizes FDA to collect fees from companies that produce certain human drug and biological products. Since the passage of PDUFA, user fees have played an important role in expediting the drug approval process. In "Regulatory Education for Industry (REdI) Annual Conference 2022", Dr. Kevin Bugin from FDA presented "PDUFA Overview and Reauthorization".
"Timely review of the safety and effectiveness of the new drug applications and biologics license applications is essential to FDA mission to protect and promote public health. PDUFA is essential to these efforts. In fact, before PSDUFA is enacted in 1992, American's access to innovative new medicines lacked behind other countries. FDA’s premarket review process was unstaffed and unpredictable, and frankly slow. Agency lacks sufficient staff to perform a timely review and lacks in procedures and standards to ensure a rigorous, consistent, and predictable process.

So to tackle these challenges Congress passed PDUFA and this authorized FDA to collect industry user fees to hire additional staff and upgrade its information technology systems, processes, and so on, in return, it committed the agency to timelines for the application review process for new drugs without compromising its high standards for new drug safety efficacy and quality and, over the years as the PDUFA program has been reauthorized now six times going into its seventh time here hopefully there have been additional enhancements."

PDUFA must be reauthorized or renewed by congress every five years. Since its inception in 1992, it has been amended six times and we are now waiting for congress to authorize the 7th amendment (PDUFA VII). Notice that each PDUFA amendment may have its own name associated with it. 

PDUFA I - Original 

PDUFA II - FDAMA (Food and Drug Administration Modernization Act) 

PDUFA III - Public Health Security and Bioterrorism Preparedness and Response Act of 2002

PDUFA IV - FDAAA (Food and Drug Administration Amendments Act of 2007)

PDUFA V - FDASIA (Food and Drug Administration Safety and Innovation Act)


There are several sister programs designed with the same purpose as PDUFA, but for different approval pathways: GDUFA (Generic Drug User Fee Amendment), BSUFA (Biosimilar User Fee Amendment), and MDUFA (Medical Device User Fee Amendment). Recently, PDUFA VII was authorized by congress, and so were these sister programs. 

Along with the approval of PDUFA, GDUFA, BSUFA, and MDUFA, the user fee rates for various types of applications are updated and released by the FDA:

PDUFA: Prescription Drug User Fee Amendments

Prescription Drug User Fee Rates for Fiscal Year 2023


GDUFA: Generic Drug User Fee Amendment

Generic Drug User Fee Rates for Fiscal Year 2023


BSUFA: Biosimilar User Fee Amendment

Biosimilar User Fee Rates for Fiscal Year 2023


MDUFA: Medical Device User Fee Amendment

Medical Device User Fee Rates for Fiscal Year 2023


For companies that are well-funded and have steady revenues, these user fees are affordable. However, these user fees could be a burden for small companies. 

For drug development in diseases with orphan drug designation, the application fees for NDAs or BLAs are waived - this is an approach to encourage the companies to develop the drugs in orphan diseases. 

FDA's guidance "User Fee Waivers, Reductions,and Refunds for Drug andBiological Products" listed the situations where the user fees can be waived.  

Monday, September 19, 2022

FMQ (FDA Medical Query) and SMQ (Standardized MedDRA Query)

For clinical trials, the safety analyses are mainly based on the analyses of the adverse events including serious adverse events. The adverse events are recorded in CRFs/eCRFs with investigators' verbatim terms (text field). Before the adverse event data can be summarized and analyzed, the verbatim terms need to be coded and standardized. The common practice is to code the adverse events based on the MedDRA dictionary and the coded terms are then summarized and analyzed by system organ class and preferred term. For a while, this approach seems to work very well. However, there are issues with this approach, mainly because different preferred terms may point to the same disease/condition. 

Last Wednesday, The FDA in collaboration with the Duke-Margolis Center for Health Policy hosted a one-day virtual meeting focused on advancing premarket safety analytics. In the morning session, FDA officers discussed the FMQ (FDA Medical Query). In the afternoon session, FDA discussed the standardized presentation of the safety data including the tables and figures for adverse event data and laboratory data. 

The FDA Medical Queries (FMQs) is a standardized approach to group preferred terms. Recognizing the limitation of the current analysis of adverse event data by preferred term, using FMQs can consolidate a medical condition with scattered preferred terms and be more likely to identify any signal of safety issues. The rationales for FDA's efforts in developing various FMQs are described in the slide below: 


FMQs were defined as the following: 

FMQs can be used to identify the safety signals that may be missed by using the conventional preferred term approach. When FMQs are adopted by the regulatory agency and the industry, FMQs (grouped term information) can be included in the ADVERSE REACTIONS Section of the Prescribing Information (or product label). The slide below illustrates a fictitious example of using FMQ term in the ADVERSE REACTIONS section of the product label. The AE table in the product label will include the mixture of the FMQ term (grouped term) and the MedDRA preferred terms. 


A real example of FMQs in the product label can be the drug called Injectafer. The tables for adverse reactions included the mixture of the preferred terms and the grouped terms (based on FDA's FMQs). 

FMQ is exactly the same concept as the SMQ (standardized MedDRA query). The SMQ was defined as the following: 

With each version of the MedDRA dictionary, a set of available SMQs will be included. Included is also the document "Introductory Guide for Standardised MedDRAQueries (SMQs)". 

Both FMQ and SMQs included narrow terms and broad terms. However, the narrow terms are more commonly used in practice. 

One natural question is: what is the difference between FMQ and SMQ? why can't we just use the SMQ? Here are a couple of slides indicating the differences between FMQ and SMQ. There are almost equal numbers of FMQs (104 FMQs for now) to SMQs (110 SMQs).


It is true that SMQs have primarily been used in pharmacovigilance, not in premarket safety assessment. I have previously written a couple of articles about the SMQs: 
One drawback of FMQ is that it is developed by the US FDA and its use and application may be limited for market authorization applications in countries outside the US. 

One thing for sure is that we will hear the term FMQ more often in the future and may see the request from FDA to present the grouped terms according to FMQs in the summary and analysis tables for AEs. 

Further reading:
