Sunday, October 10, 2021

Recommendations for DMC: How Many Statisticians Need to be Involved in Successful DMC Process?

Independent data monitoring committee (iDMC) is more commonly used in clinical trials than before for various reasons. For innovative and complex trials, an iDMC is usually a must-to-have external committee. For clinical trials containing the adaptations, interim analyses, iDMC can provide a way to review the unblinded data to recommend some critical suggestions about the ongoing clinical trial while maintaining the study integrity. In some cases, the sponsor just wants to have an independent body to oversee the study for extra credibility. 

There are plenty of regulatory guidelines for the general principles for establishing and operating a DMC. There are also recommendations from the industry/academic for successful DMC implementation. 

"What are some of the key factors that a sponsor should consider when deciding whether to suspend or continue an ongoing study or to initiate a new study during the COVID-19 public health emergency?

Involvement of a study’s DMC, if one has been established, can provide support for the assessments discussed above. Since a primary responsibility of the DMC is assuring the safety of participating trial participants, the DMC’s assessment of the impact of modifications of trial conduct due to COVID-19 on patient safety is important to consider."

When planning for a DMC, multiple statisticians need to be involved - at least three statisticians (blinded and unblinded statisticians) need to play a role in the successful conduct of a DMC. The diagram below lists three different statisticians that are needed for a successful DMC.  


DMC Statistician: 
  • One of the DMC members
  • the voting member
  • with biostatistical expertise, applying the statistical methods in the monitoring process. 
  • understands the complex clinical trial designs (group sequential design, adaptive design, ...), familiar with the application of the stopping rules, Type I error issue, multiplicity issue. 
  • According to FDA's guidance on DMC: "Most DMCs are composed of clinicians with expertise in relevant clinical specialties and at least one biostatistician knowledgeable about statistical methods for clinical trials and sequential analysis of trial data."
  • usually unblinded and have access to the unblinded data 
Trial Statistician: 
  • clinical trial study team member and can not be the DMC member
  • can attend the open session of the DMC meetings; can't attend the closed session of the DMC meetings
  • only have access to the blinded or pooled study data during the study
  • responsible for the statistical section of the study protocol including the statistical methods for group sequential design, adaptive design, stopping rules... 
  • responsible for simulations (if needed) to address questions about the alpha I error spending, multiplicity issue
  • maybe the author to develop the statistical analysis plan for DMC and for interim analysis
  • provide the blinded data sets to the SDAC (reporting) statistician
  • may work with SDAC statistician and review the blinded statistical outputs from the SDAC statistician to ensure the correctness of the statistical package (blinded version)
SDAC Statistician:
  • statistician on the Statistical Data Analysis Center (SDAC) - in industry, this is called reporting statistician or independent statistician. 
  • non-voting member
  • primary responsibility is to prepare the statistical outputs (tables, listings, and figures) for DMC. perform the analyses on unblinded interim data and provide the results of comparative interim analyses.
  • Reporting statistician will receive the data sets from the data management group and receive the randomization information (unblinded information) directly from the IRT (interactive response technology) group
  • Reporting statistician sends the statistical package (unblinded) to DMC for review. 
  • Reporting statistician is usually unblinded.
  • reporting statistician may have a programming team to help with generating the data sets, tables, listings, and figures. Anybody who is working with the reporting statistician needs to follow the same rules that are applicable to the reporting statistician. 
  • attend the DMC meeting (open and close sessions) and provide explanations for any issues raised by DMC members related to the DMC statistical outputs  
As indicated in the diagram above, the trial statistician and reporting statistician may have close discussions and interactions while working on the blinded data. The reporting statistician and the DMC statistician may also have close interactions while working on the unblinded data. There should be no direct interaction or very little interaction between the trial statistician and the DMC statistician (usually the interaction may be limited to the initial administrative meeting and the open session at the scheduled DMC meetings).

FDA guidance on DMC contains a lengthy section to discuss the reporting statistician's roles in the DMC process. FDA is very concerned about the potential risks that statisticians who conduct the interim analyses may comprise the integrity of the clinical trial. The primary trial statistician should not be the one who conduct the interim analysis. The statistician who conducts the interim analysis should not be in the sponsor's organization.  


Friday, October 08, 2021

Serial Blood Sample Timepoints for Comparing Pharmacokinetics Profiles Between Two Different Dose Frequencies

It is very common in the drug development process that the dosing frequency needs to be studied. The dosing frequency is usually based on the pharmacokinetic profiles. In multiple-dose studies, the dose frequency decides the dosing interval: QD for once daily, BID for twice daily, and TID for three times daily. 

Usually, to compare the pharmacokinetic profiles, serial blood samples will be taken over the period of the dosing interval (between the previous dose and the next dose).  The area under the curve (AUC) will then be calculated over the dosing interval (commonly denoted as tau).
  • For QD dose, Tau = 24 hours, AUCtau is AUC[0-24 hours]
  • For BID dose, Tau = 12 hours, AUCtau is AUC[0-12 hours]
  • For TID dose, Tau = 8 hours, AUCtau is AUC[0-8 hours]
It will be straightforward to select the Pharmacokinetics (PK) sampling time points if two drugs/formulations to be compared have the same dose interval. However, in practice, we often need to compare the PK profiles for two drugs/formulations with different dose intervals, for example, between QD versus BID, or between QD versus TID.  

For comparison of PK profiles between QD dose, BID dose, and TID dose, one will need to compare AUC[0-24 hours] with 2 x AUC[0-12 hours] for BID and with 3 x AUC[0-8 hours] for TID.

For QD dosing, serial PK samples will be collected over 24 hours. For BID dosing and TID dosing, there are two different ways to decide the serial PK samples:

For BID dosing,   
  1. serial PK samples can also be collected over 24 hours, the calculated AUC[0-24 hours] can directly be compared with AUC[0-24 hours] from QD dosing even though there will be an extra dose at the middle of the 24 hours period. 
  2. serial PK samples can be collected over 12 hours, then the calculated AUC[0-12 hours] needs to be multiplied by 2 in order to be compared with AUC[0-24 hours]
For TID dosing, 
  1. serial PK samples can also be collected over 24 hours, the calculated AUC[0-24 hours] can directly be compared with AUC[0-24 hours] from QD dosing even though there will be two extra doses during the 24 hours period. 
  2. serial PK samples can be collected over 8 hours, then the calculated AUC[0-8 hours] needs to be multiplied by 3 in order to be compared with AUC[0-24 hours]
In a study by Dawra et al, "A PK/PD study comparing twice-daily to once-daily dosing regimens of ertugliflozin in healthy subjects", the blood samples were collected for QD and BID as the followings:
For each period, blood samples for PK analysis were collected for QD dosing as follows: on days 4, 5, and 6 before administration of the morning dose, and at 0.5, 1, 2, 3, 4, 8, 12, and 24 hours after the morning dose on day 6. For BID dosing, blood samples were collected at 0.5, 1, 2, 3, 4, 8, 12 (preevening dose), 12.5, 13, 14, 15, 16, 20, and 24 hours after the morning dose on day 6.            
Notice that the blood samples for BID were collected at 0.5, 1, 2, 3, 4, 8, 12 post the morning dose and then 0.5, 1, 2, 3, 4, 8, 12 post the evening dose. 

The PK profiles for OD and BID doses are displayed in the figures below: 


This approach of the PK blood sampling schema will require an extensive number of blood draws. For the BID dose, two serial PK samples need to be drawn; for the TID dose, three serial PK samples need to be drawn. The advantage is to capture the potential impact of the circadian and diurnal cycles. 

In some situations, too many blood sample draws may not be practical, and an alternative approach needs to be taken. For example, in pediatric PK studies, the number of blood sample draws may be limited due to the restriction in the total blood volume. 

One of the alternative approaches is to draw the serial PK samples only for one dose interval, not draw additional serial PK samples after the next dose. For example, for the BID dose, the serial PK samples are drawn over 12 hours period assuming that the PK profiles after the evening dose will be the same as the PK profiles over 12 hours post the morning dose. The AUC[0-12 hours] needs to be multiplied by 2 before comparing it to the AUC[0-24 hours] for QD dose. 

In a study to compare the IVIG (every four weeks dosing schedule) and SCIG (weekly dose schedule), the serial PK samples for IVIG were drawn over 4 week period, and the serial PK samples for SCIG were drawn over 1 week period (instead of 4 week period). To compare the AUCs between IVIG and SCIG, the AUC[0-7 days] was multiplied by 4 before comparing it to the AUC[0-28 days]. With this approach, the next three weekly intervals are assumed to have the same PK profiles as the first weekly interval. We can also say that the PK profiles for the next three intervals (dotted lines) are projected or simulated.  This approach was accepted by the FDA and PK results were included in the product label. The PK profiles for IVIG and SCIG are displayed below (the dotted portion for SCIG was projected). 


Monday, September 27, 2021

Advancing the Development of Pediatric Therapeutics (ADEPT) - FDA Workshops on Pediatric Drug Developments

Each year, the FDA's Division of Pediatrics and Maternal Health in collaboration with the University of Maryland CERSI organized an annual public workshop to discuss the issue related to pediatric drug development. Starting in 2014, it has organized 7 public workshops (no event for 2020 due to Covid-19). 

           Advancing the Development of Pediatric Therapeutics (ADEPT)

ADEPT 7

2021

Complex Innovative Trial Design

"Advancing the Development of Pediatric Therapeutics Innovative Trail Design"

ADEPT 6

2019

Pediatric Patient Perspectives


Pediatric Clinical Trial Endpoints for Rare Diseases With a Focus on Pediatric Patient Perspectives

NOVEMBER 12, 2019

ADEPT 5

2018

Pediatric Pharmacovigilance

Advancing Pediatric Pharmacovigilance Public Workshop

AUGUST 13, 2018

ADEPT 4

2017

Big data


Application of "Big Data" to Pediatric Safety Studies

ADEPT 3

2016

Long-Term Pediatric Safety Studies

Successes and Challenges of Performing Long-Term Pediatric Safety Studies:

Pediatric Drug Development Regulatory Considerations

International Collaborations in Pediatrics: FDA and EMA growing together

International Considerations for Pediatric Master Protocols


ADEPT 2

2015

Long-term Neurocognitive Development in Pediatrics

Evaluation of Long-term Neurocognitive Development in Pediatrics

ADEPT 1

2014

Pediatric Bone Health


For this year (2021), the 2-day public workshop was titled “Advancing the Development of Pediatric Therapeutics Complex Innovative Trial Design”. The purpose of the workshop was to discuss opportunities for leveraging complex and innovative trial designs, understand the challenges with their applications, and develop solutions on how challenges in the designs can be overcome. 

The workshop specifically focused on two topics of interest: 
  • bridging biomarkers in pediatric extrapolation 
  • Bayesian techniques in pediatric studies. 
In addition, the workshop allowed for an open dialogue around the use of these approaches among regulators, industry, academia, and patient organizations.

The presentation slides & webcast video links from the workshop are now all available.

SEPTEMBER 1 - 2, 2021


Saturday, September 11, 2021

Afghan Withdrawal and Accelerated Approval for Aduhelm

These two topics seem to be irrelevant at all, but have one thing in common: changing the subjects when the decision is questioned.

For the US withdrawal from Afghanistan, the decision to withdraw from two decades of war is the right decision and welcomed by the majority of the Americans. However, the execution of the withdrawal was a disaster. The execution of the withdrawal is not properly planned, botched, entirely a failure no matter how the Biden administration tries to spin and change the subject. When questioned by the reporters, the Biden administration keeps mentioning how correct the decision of withdrawal from Afghanistan is and avoids mentioning why the execution of the withdrawal goes so wrong.
Changing the subject is also the theme in the controversial approval of Aduhelm for the treatment of Alzheimer's disease through the 'accelerated approval' pathway. The full story of the Aduhelm approval is very well captured in a New York Times article "How an Unproven Alzheimer's Drug Got Approved" and ‎NEJM Interview: Dr. Gil Rabinovici on the FDA’s controversial approval of a new treatment for Alzheimer’s disease. on Apple Podcasts. 

'Accelerated approval' is a valid pathway for approving a drug based on the surrogate endpoint without waiting for the results from the lengthy confirmatory trial to demonstrate the clinical benefit.  "Accelerated approval" was one of the regulatory approval pathways listed in FDA's guidance for industry "Expedited Programs for SeriousConditions – Drugs and Biologics"


Facing the mounting criticisms, FDA officials published the papers to defend their decision - Approval of Aduhelm through the 'accelerated approval' pathway is the right decision. They changed the subject here. Rather than arguing if approval of Aduhelm is the right decision, they argued if 'accelerated approval' is an appropriate approval pathway. 
The controversy is not about 'accelerated approval', it is about how the 'accelerated approval' is used in the approval of Aduhelm. 

Accelerated approval is appropriate if the following qualifying criteria are met: 
  • Serious Condition
  • Meaningful Advantage Over Available Therapy
  • Demonstrates an Effect on an Endpoint That Is Reasonably Likely to Predict Clinical Benefit
In Aduhelm's situation, the third criterion was not met. The two confirmatory trials had already been completed and indicated the inclusive results in clinical benefit. There is no evidence to conclude the biomarker (beta-amyloid) will be 'reasonably likely to predict clinical benefit.' 

'Accelerated approval' is a valid pathway for drug approval for a serious condition, however, it can't be applied to a drug approval:
  • as a remedy approach (when clinical benefit had been shown to be inclusive)
  • retrospectively applied (when the lengthy confirmatory trials had already been completed)
  • against the pre-specification rule (i.e., accelerated approval pathway had been discussed and agreed with the agency prior to the BLA/NDA submission)
  • for pivotal studies that had been discontinued early due to futility 
  • based on results largely from the post-hoc, sub-group analyses
  • against the consensus objection from the FDA advisory committee members. 

No wonder there are so many controversies after FDA's decision to approve Aduhelm, The story is continuing,...
The New York Times (9/2, Belluck) reports two congressional committees “investigating the controversial federal approval of Biogen’s Alzheimer’s drug, Aduhelm [aducanumab], demanded extensive information and documents from the Food and Drug Administration in a letter released on Thursday, making it clear that the committees’ leaders are troubled by unusual actions the agency took in the course of evaluating and approving the drug.” The letter said the agency “granted accelerated approval for the drug despite concerns raised by experts – including the agency’s own staff’ and members of its independent advisory committee. ... We are also concerned by reports of unusual coordination between F.D.A. and Biogen throughout the drug’s approval process.” The Times adds, “While some Alzheimer’s experts did support the approval, given that there are so few therapies available for the devastating condition, many are concerned that the evidence does not convincingly show the drug can provide any benefit. There is also concern because the medication can cause brain swelling or brain bleeding.”
Afgan Withdrawal: the decision is right, execution is not!
Aduhelm Approval: accelerated approval is a valid pathway, the application of accelerated approval in Aduheml approval is not!

Sunday, August 29, 2021

Drug names: brand name, proprietary name, trade name, generic name, and sponsor's drug code

Every Saturday, my favorite radio show is "Wait Wait... Don't Tell Me! | WUNC". In yesterday's episode, the host made fun of the brand name ('Comirnaty') of Pfizer/BioNTech Covid (Listen: 46.17 minutes).

Covid vaccines from Pfizer/BioNTech, Moderna, and J&J have become the household name in just about a year or so and have been administered to millions and millions of people under FDA's Emergency Use Authorization (EUA). Under the EUA, these vaccines are just called and differentiated by the company's name: Pfizer vaccine, Moderna vaccine, and J&J vaccine. However, when the vaccine (or any drug) is formally approved, according to the regulation, it must have a brand name - in the case of Pfizer/BioNTech Covid vaccine, the brand name is now 'Comirnaty'.

The meaning behind the name 'Comirnaty': Comirnaty is an agglomeration of the words “Covid-19 immunity” and “mRNA,” the latter indicating the technology that makes the vaccine work. As a whole, the word is intended to evoke “community,”

This brings a question about the drug names: the difference between the brand name and the generic name and how to record the drug names in clinical trials. According to the CDASH, the case report form will include a form for concomitant medication including the questions like

"What was the term for the medication/therapy taken?

or

"What was the term for the medication taken?"

Concomitant medications used by the study participants prior to the trial or during the trial period should all be recorded. Usually, there is no restriction on the medication term to be recorded. Either brand name or generic name can be recorded. 

The brand name of a medication is the name given by the company that makes the drug and is usually easy to say for sales and marketing purposes. The brand name may also be called the trade name. In FDA's guidance, the brand name is called proprietary name. The proprietary name of a drug product is its brand name. 

The generic name, on the other hand, is the name of the active ingredient. Generic drugs are copies of brand-name drugs that have exactly the same dosage, intended use, effects, side effects, route of administration, risks, safety, and strength as the original drug. In other words, their pharmacological effects are exactly the same as those of their brand-name counterparts. In FDA's guidance, the generic name may be called 'nonproprietary name' or 'proper name' for biological products. For biological products, the term proper name means the nonproprietary name designated by FDA in the license for a biological product licensed under the PHS Act. See also 105 21 CFR 600.3(k).

For drugs that make it all the way through development, testing, and regulatory acceptance, the pharmaceutical company then gives the drug a trade name, which is a standard term in the pharmaceutical industry for a brand name, trademark name, or proprietary name. The proprietary name must be approved by the FDA and included in the product label. FDA has its guidance for industry to govern the brand name approval process "Best Practices in DevelopingProprietary Names for HumanPrescription Drug Products".

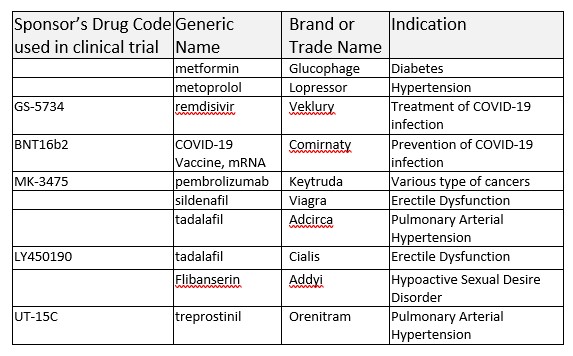
During the development stage, sponsors of the clinical trials may use their code for the compound or drug in the development. These drug codes will not be used when a drug is approved. For example, the famous drug from Merck 'pembrolizumab' has its own code MK-3475 that can be used in the clinical development stage and registered in clinicaltrials.gov, but will not be used as the name once the product is approved or marketed. Sponsor's drug code: MK-3475 - > generic name: pembrolizumab -> brand name: Keytruda. Similarly, Gilead's COVID-19 treatment drug has sponsor's drug code GS-5734 -> generic name: remdesivir -> Veklery. Pfizer/BioNTech's COVID-19 vaccine has sponsor's drug code: BNT16b2 -> generic name: COVID-19 Vaccine, mRNA -> brand name (proprietary name): COMIRNATY.

Here are some examples of the sponsor's drug code, generic drug name, brand drug name, and the corresponding indications.

When recording the drug name in clinical trials, either brand name or generic name can be recorded, but not the drug code used by the sponsors. 

Before the statistical analyses of the concomitant medication data, the data management group will perform appropriate medical coding activities to map the recorded brand name or generic name to the corresponding ATC classifications according to WHODrug-Global dictionary. 

Retire Statistical Significance and p-value? - Revisited

In 2019, there was a public debate about the use or misuse of statistical significance and p-values. I wrote a post about it "Retire Statistical Significance and p-value?"

Obviously, the hypothesis testing, statistical significance, and p-value are still the cornerstone of our clinical trials, the basis for judging if a clinical trial is a success, and the basis for the decision-making for regulatory approvals by the FDA and other regulatory authorities. 

In the latest issue of AMSTATNews and also the Annals of Applied Statistics, there is an article "The ASA President’s Task Force Statement on Statistical Significance and Replicability". The statements confirmed that the significance and p-values are here to stay. 
"P-values are valid statistical measures that provide convenient conventions for communicating the uncertainty inherent in quantitative results. Indeed, p-values and significance tests are among the most studied and best understood statistical procedures in the statistical literature. They are important tools that have advanced science through their proper application."

"p-values and significance tests, when properly applied and interpreted, increase the rigor of the conclusions drawn from data. Analyzing data and summarizing results are often more complex than is sometimes popularly conveyed. Although all scientific methods have limitations, the proper application of statistical methods is essential for interpreting the results of data analyses and enhancing the applicability of scientific results."

I would say the following about the significant tests and p-values:

  • We embrace it, not abandon it. 
  • We focus on the appropriate use and interpretation
  • We should not become the slave of the p-values

A quote from  Alfred Marshall, 1885:

"The most reckless and treacherous of all theorists is he who professes to let facts and figures speak for themselves, who keeps in the background the part he has played, perhaps unconsciously, in selecting and grouping them."

Monday, August 09, 2021

Randomized Withdrawal Design in Practice - Story of the HARMONY Trial

In previous posts, we discussed the "Randomized Withdrawal Design and Randomized Discontinuation Trial" and "Randomized Withdrawal Design - Examples for Defining the Criteria for Run-in and Randomized Withdrawal Periods".

Randomized Withdrawal Design (RWD) was discussed in FDA guidance "Enrichment Strategies for Clinical Trials to Support Determination of Effectiveness of Human Drugs and Biological Products" as one of the enrichment strategies and enable us to minimize the sample size of the study while demonstrating the efficacy of the experimental drug. 
"In a randomized withdrawal study, patients who have an apparent response to treatment in an open-label period or in the treatment arm of a randomized trial are randomized to continued drug treatment or to placebo treatment. Because such trials generally involve only patients who appear to have responded, this is a study enriched with apparent responders, an empiric strategy. The study evaluation can be based on signs or symptoms during a specified interval (e.g., BP, angina rate), on recurrence of a condition that had been controlled by the drug (e.g., depression), or on the fraction of patients developing a rate or severity of symptoms that exceeds some specified limit (i.e., a failure criterion). "

Even though the FDA encourages the use of the randomized withdrawal design in clinical trials, the use of RWD is still very limited, especially in pivotal, confirmatory studies. The reluctance in using the RWD is usually due to the safety concern - it will be perceived as unethical to discontinue the experimental treatment in the Placebo group when the experimental treatment has just been shown to be effective. Another concern is the size of the safety database - there is usually a sufficient number of patients exposed to the experimental drug so that the safety can be adequately assessed (see a previous post "The Size of Safety Database In Drug Development Program")

In the recent issue of the New England Journal of Medicine, the results of the HARMONY study (sponsored by Acadia Pharmaceuticals) were published: Tariot et al "Trial of Pimavanserin in Dementia-Related Psychosis". While the term 'randomized withdrawal' was not explicitly used in the study, the HARMONY study was a randomized withdrawal study and was described as the following:  
"a phase 3, double-blind, randomized, placebo-controlled discontinuation trial involving patients with psychosis related to Alzheimer’s disease, Parkinson’s disease dementia, dementia with Lewy bodies, frontotemporal dementia, or vascular dementia. Patients received open-label pimavanserin for 12 weeks. Those who had a reduction from baseline of at least 30% in the score on the Scale for the Assessment of Positive Symptoms–Hallucinations and Delusions (SAPS–H+D, with higher scores indicating greater psychosis) and a Clinical Global Impression–Improvement (CGI-I) score of 1 (very much improved) or 2 (much improved) at weeks 8 and 12 were randomly assigned in a 1:1 ratio to continue receiving pimavanserin or to receive placebo for up to 26 weeks. "
As we can see from the study design diagram below, all patients received pimavanserin during the open-label period. Those subjects who had responses to the pimavanserin (i.e., reduction in SAPS-H+D) were randomized to continue the treatment of pimavanserin or withdraw the treatment of pimavanserin (i.e., receiving the placebo). 


HARMONY Study protocol and SAP were posted on clinicaltrials.gov.  

Study Protocol  [PDF] July 16, 2010
Statistical Analysis Plan  [PDF] August 5, 2014

With the HARMONY study using a randomized withdrawal design, the sponsor was able to demonstrate the efficacy of pimavanserin in treating patients with dementia-related psychosis. The reduced sample size due to the use of the randomized withdrawal design was further reduced after the sponsor stopped the study early for positive efficacy. The sponsor subsequently submitted the sNDA for pimavanserin in treating patients with dementia-related psychosis. Unfortunately, they received a complete response letter from FDA citing the reasons not related to the study design but related to the insufficient sample size for certain sub-groups. 

Wednesday, July 28, 2021

FDA Regulatory Education for Industry (REdI) - Learning about FDA and Regulatory Science

FDA had their annual conference “FDA Regulatory Education for Industry (REdI)” last week. The REdI conference features three medical product center tracks: Drugs (CDER), Devices (CDRH), and Biologics (CBER). 

The recorded presentations by different tracks (drug, device, biological,...) are available on FDA's website and the conference agenda for this 5-day event is listed here. 

REdI presentations provide opportunities to learn directly from the FDA’s regulatory experts in medical product centers: drugs, devices, and biologics. This course is designed to provide participants with a strong, basic foundation in the FDA’s regulatory requirements.

The recording of the REdI conference are also posted on Youtube and separated by days 1 - 5.

Day 1: 


Day 2:


Day 3:


Day 4: 

Day 5: 


In Day 1 presentation by Dr. Bugin, the reorganized structure for various divisions under the Office of New Drug (OND) is revealed. 


Sunday, July 25, 2021

Maximum Tolerable Dose (MTD) and Dose-Limiting Toxicities (DLTs)

According to Wiley Encyclopedia of Clinical Trials, the maximum tolerable dose (MTD) is defined as: 

The “Maximum Tolerable Dose” (MTD), also known as the “Maximum Tolerated Dose” or the “Maximally Tolerated Dose”, is defined as the dose that produces an “acceptable” level of toxicity or that, if exceeded, would put animals or patients at “unacceptable” risk for toxicity. Besides determining animal toxicology, establishing the MTD is the main objective of Phase I clinical trials, mostly in cancer and HIV treatment in which relatively high doses of drugs are usually chosen to achieve the greatest possible beneficial antitumor effect. Definition of the MTD usually relies on the sample, as MTD is defined as the dose level at which more than two patients over six experienced dose-limiting toxicity (DLT). More recently, the MTD has been defined as the dose that produces a certain frequency of DLT within the treated patient population. In this framework, the MTD is estimated from the data using Bayes or maximum likelihood inference. In all these designs, the MTD is established for one initial administration or treatment course of a cytotoxic experimental agent, ignoring efficacy. To address these issues, the maximum tolerated schedule and the most successful dose have been proposed to be used rather than a conventional MTD. Finally, the concept of MTD that uses toxicity as a surrogate endpoint for efficacy in cytotoxic Phase I trials has been also controversial. Interests in alternatives to MTD have gained recently when dealing with new cytostatic agents that may produce relatively minimal organ toxicity, compared with standard cytotoxics. New optimal doses should be defined in the near future.

The clinical trials with the objective of determining the MTD are designed as dose-escalation studies with patients enrolled into the low dose group and then gradually into the high dose group. The patients who are enrolled under the same dose level below to the same dose cohort. The determination of the MTD relies on the identification of the dose-limiting toxicities (DLTs). Prior to escalating the dose cohort, the safety and tolerability in the previous cohort will be assessed and evaluated. 

According to NCI, DLTs are defined as side effects of a drug or other treatment that are serious enough to prevent an increase in dose or level of that treatment. In early-phase clinical trials, DTLs are defined so that the escalation of the dose cohort to the higher dose level can be determined based on the observed # of DTLs, which are subsequently used to determine the maximum tolerable dose (MTD). 

The dose-escalation study for determining the MTD is the most common first-in-human study design in oncology studies. The DTLs are usually defined as grade 3 or above drug-related adverse events defined by the common toxicity criteria for AEs (CTCAE) maintained by the National Cancer Institute (NCI). 

In non-oncology studies, the CTCAE criteria can still be used to define DTLs. But we also see some non-oncology studies with the customer-defined DLTs criteria.

Here are some examples of how the DTLs are described in oncology clinical trials with MTD as the purpose.  

A Multicenter Phase I Gene Therapy Clinical Trial Involving Intraperitoneal Administration of E1A-Lipid Complex in Patients with Recurrent Epithelial Ovarian Cancer Overexpressing HER-2/neu Oncogene

Toxicity during therapy was categorized as unrelated to, probably, possibly, or definitely related to E1A lipid complex. The dose-limiting toxicity was defined as the highest dose at which at least 2 of the 6 patients experienced National Cancer Institute Common Toxicity Criteria grade 3 or 4 drug-related toxicity during the course of therapy. Maximum tolerated dose was defined at one dose level below dose-limiting toxicity

Intra-arterial administration of a replication-selective adenovirus (dl1520) in patients with colorectal carcinoma metastatic to the liver: a phase I trial
Dose escalation proceeded from 2 × 10⁸ to 2 × 10¹² particles without occurrence of any dose-limiting toxicities. Specifically, no treatment-emergent clinical hepatotoxicity occurred during dose-escalation, despite pre-existing liver abnormalities due to intrahepatic metastases in over half of the patients at baseline. Transient low grade (1– 2) transaminitis was documented in three patients (following single agent virus) and was classified by the investigator as ‘possibly attributable’ to ONYX-015 (6 × 10¹¹ and 2 × 10¹² particles); the laboratory abnormalities resolved within 12 days and did not reoccur after subsequent treatments. Four patients had liver-related adverse events reported (hyperbilirubinemia) that were classified as ‘unrelated’ to ONYX-015 and were associated with intrahepatic tumor progression. The highest dose administered (2 × 10¹² particles) was shown to be well-tolerated in three patients. The 2 × 10¹² particle dose level therefore appears to be well-tolerated, and the maximum dose that could be administered based on manufacturing capabilities was the MTD for the study

Redefining Dose-Limiting Toxicity

Dose-limiting toxicities (DLTs) traditionally are defined by the occurrence of severe toxicities during the first cycle of systemic cancer therapy. Such toxicities are assessed according to the National Cancer Institute’s Common Terminology Criteria for Adverse Events (CTCAE) classification, and usually encompass all grade 3 or higher toxicities with the exception of grade 3 nonfebrile neutropenia and alopecia. This broad definition dates back to the development of conventional cytotoxic chemotherapeutic agents, and is not applicable to the toxicity profile of modern molecularly targeted therapies (MTTs), which now constitute the vast majority of drugs evaluated in phase 1 trials. Despite this shift in drug development, the old definition of DLT is still used for most clinical trials. However, a few clinical trials are beginning to update their definition of DLT, and now tend to add variations to that common DLT definition backbone. The most frequent changes include the addition of some a priori untreatable or irreversible grade 2 toxicities (eg, neurotoxicities, ocular toxicities, or cardiac toxicities), prolonged grade 2 toxicities (ie, grade 2 toxicities lasting longer than a certain period), or the prolongation of the DLT period. However, these changes are still rare and most phase 1 clinical trials still use the traditional DLT definition.

Lenalidomide in Treating Patients With AIDS-Associated Kaposi's Sarcoma
Toxicities will be graded according to the National Cancer Institute (NCI) Common Terminology Criteria for Adverse Events (CTCAE) Version 4.0. Using a 3+3 design, the MTD is defined as the level at which 0/6 or 1/6 patients experiences at dose-limiting toxicity in the first cycle.

Here are some examples of how the DTLs are described in non-oncology clinical trials with MTD as the purpose.  

The LIPid Intensive Drug Therapy for Sepsis - Pilot (LIPIDS-P) Phase I/II Trial
LIPid Intensive Drug therapy for SepsisPilot (LIPIDS-P): Phase I/II clinical trial protocol of lipid emulsion therapy for stabilising cholesterol levels in sepsis and septic shock

Safety and Tolerability Study of Allogeneic Mesenchymal Stem Cell Infusion in Adults With Cystic Fibrosis (CEASE-CF)

Dose limiting toxicity (DLT), triggered by occurrence in the first 24 hours after hMSC infusion of grade ≥3 infusion-related allergic toxicities [ Time Frame: 24 hours ]

 Phase 1b Study of PD-0332991 in Combination With T-DM1(Trastuzumab-DM1)

Toxicity will be assessed using the Common Terminology Criteria of Adverse Events (CTCAE) version 4.0 grading scale. Dose- limiting toxicity-DLT is defined as any drug-related grade 3 non-hematologic toxicity or grade 4 hematologic toxicity lasting >28 days after the last day of therapy. If two patients experience drug-related DLT, the maximal tolerated dose (MTD) for the combination in HER2-positive breast cancer patients has been exceeded, enrollment to that dose will stop, and the next lower dose will be designated the MTD. An additional 15 patients will be treated at the MTD or the maximal 200mg po daily PD-0332991 dose in combination with T-DM1 to confirm safety. Treatment cycles will continue until disease progression or withdrawal from study.
Histone Deacetylase Inhibitor LBH589 in Addition to Corticosteroids in Patients With Acute Graft Versus Host Disease (GVHD)
Dose limiting toxicity (DLT) is defined by the occurrence of Common Toxicity Criteria (CTC) grade 3 or greater toxicity that is unexpected with transplantation, except for hematological toxicity, where DLT is defined as absolute neutrophil count (ANC) <750, and for those participants who were platelet transfusion independent is defined as platelets <10 K.
We can identify the clinical trials on clinicaltrials.gov with the purpose of identifying the MTDs and DLTs. The vast majority of these studies are oncology studies or studies in serious conditions - these studies are usually conducted in patients (not healthy volunteers) and must be registered on clinicaltrials.gov even it is a phase I study - the phase I studies in healthy volunteers are exempted from the clinicaltrias.gov registration. 

Sunday, July 18, 2021

Imputation of partial dates for adverse events, concomitant medications, and disease diagnosis

Many date variables are collected in the clinical trial database. The date variables include date of birth, date of disease diagnosis, date of medical history onset, start and stop date of adverse events, start / stop date of concomitant medications, ......

It is not uncommon that the partial dates may be collected where the partial dates mean that at least one of the components (day, month, or year) is missing. 

Partial date for date of birth is not because the subjects don't remember their birth date, is because the data security law prevents the sponsors from collecting the date of birth information in certain countries (especially in Germany). 

In statistical analyses, the partial dates need to be handled or imputed for the purpose of allocating the event (adverse events, concomitant medication) into the appropriate categories (treatment-emergent adverse events, prior medications, concomitant medications added during the study,...) or calculating the duration of the events (duration from the disease diagnosis to the study start).

For clarity, the algorithm and rules for imputing the partial dates need to be specified in the statistical analysis plan (SAP). There is no regulatory guidance about which algorithm and rules will be appropriate when imputing the partial dates. Different companies may have different rules when imputing partial dates. In general, the rules will be adequate as long as it is on the conservative side, for example, if an adverse event has a partial or missing start date and can't be determined if it occurs before the first dose of the study drug, the adverse event will be classified as 'treatment-emergent adverse event'. 

Partial date imputation is always a single imputation - the missing day or missing month will be replaced with a fixed day or month based on the imputation algorithm. The candidates for replacing the missing day could be: the first day of the month, the last day of the month, the day of the first dose of the study drug. The candidates for replacing the missing day and month could be Jun 30 of the year or July 1 of the year. 

Usually, if all day, month, and year are missing, the missing date will not be imputed. The adverse events with missing onset date will be classified as 'treatment-emergent AEs' and the concomitant medication will be classified as 'on treatment medications' (i.e., to be included in summaries of concomitant medications during the study). 

Below are a list of algorithm and rules for imputing the partial dates for adverse events and concomitant medications:

In an SAP for a Pfizer phase I study, if the day of the month is missing, the 1st day of the month is used. 


In a Novartis study SAP, the rather complicated algorithm was proposed for imputing the partial dates for adverse events and concomitant medications:


In a study by Johnson & Johnson, the appended SAP specified the rules for imputing the partial dates for adverse events, concomitant medications, and for disease diagnosis as the following: 


In a study by ChemoCentryx in NEJM, the appended SAP described the imputation rules for partial dates for adverse events and concomitant medications as the following: 


In the paper "Partial Dates; decisions and implications of handling partially missing dates" by Bowman, the following rules were stated for imputing the partial dates for adverse events and concomitant medications. 

Missing Adverse Event Start and Stop Dates date:

There are two options available. The partial start date may be set to the first of the month or to equal the study medication start date. As previously discussed, the first option would indicate the adverse event began prior to the study medication. However, the second option, setting the start date of AE1 to the study medication start date will suggest the adverse event had a short duration, as the adverse event end date is also defined as June 2006, but began during the treatment period of the study drug. Although the second option is not ideal, as AE1 may have had a longer duration, it is more conservative to associate the adverse event start with a date during study medication. Another solution to consider is not to impute a date at all but merely to assign a study phase to the start of the adverse event. In this example, a phase of "treatment" could be allocated to the start of teh adverse event, which would ensure it was classed most conservatively, without defining an actual date to the start of the adverse event. 

Concomitant Medications:

Subject has a partial concomitant medication start date of “--Apr2006” (see figure 1). As discussed above, missing start dates may be set to the first of the month, which is shown under option 1. However, this then pushes the concomitant medication to starting before the first dose of the Study Medication (15Apr2006) and would suggest that the Study Medication had no involvement with the concomitant medication being taken. Is this really the most conservative approach? If not is there an alternative? The missing concomitant medication start date could be set to equal the first dose of Study Medication, options 2. This option allows the concomitant medication to be classed as an on-treatment medication, and is therefore the most conservative.  


Monday, July 12, 2021

Human Plasma-derived Products - Protein Therapies for Rare Diseases

I recently listened to a podcast from NPR's planet money "Blood Money". It discussed why only the U.S. and a few other countries allow companies to pay people for blood (or precisely the plasma) - the materials for many life-saving protein therapy products for rare diseases. Please listen to the podcast or read the transcripts of the podcast. 

Blood Money

We all heard or experienced blood donation which is usually voluntary by the donor with no monetary incentives. The Plasma donation is different and donors are paid for donating their plasma. So the first question we need to know what the difference between the (whole) blood and the plasma. Here is a table for comparison:

Whole Blood

Plasma

This red bodily fluid is composed of red cells, white cells, plasma, and platelets. It supplies oxygen and essential nutrients to cells and tissues in the body and removes waste materials like carbon dioxide and lactic acid.Plasma is the clear, straw-colored liquid component found in the blood. It is made up of 90% water and carries nutrients, minerals, hormones, and proteins to parts of the body that need it. Plasma also contains antibodies that help fight infections and proteins including albumin and fibrinogen that help maintain serum osmotic pressure.
With red cells, white blood cells, and platelets in itWith red cells, white blood cells, and platelets removed


plasma is collected through a process known as plasmapheresis. Plasmapheresis is a method of removing and separating plasma from whole blood via an apheresis machine.

After Plasma is separated from the whole blood, the red blood cells and other cellular components are returned to the doner’s body
Whole blood is commonly transfused in its original form in an effort to treat injuries and illnesses. It can be also be separated into its individual components and used to treat conditions including cancer and blood disorders.Plasma, on the other hand, is typically used as a starting material to manufacture commercial drugs known as plasma-derived products. These plasma-derived products serve as lifesaving therapies for patients living with immune deficiencies and autoimmune diseases.


Human plasma is a treasure and contains many enzymes and antibodies that can be extracted and manufactured as medicines for many rare diseases. Human plasma products (also called plasma-derived products or fractionated plasma products) are highly regulated by the FDA - Office of Blood Research and Review under the Center for Biological Evaluation and Research (CBER). The drugs manufactured from human plasma (so-called plasma-derived products) need to go through the same process as other biological products and Biological License Application (BLAs) needs to be approved by the FDA for market authorization. Human plasma-derived products have been approved to be used in treating diseases in various indications in immunology area, enzyme replacement/augmentation therapies, neurology, pulmonary, hemostasis, ...... Some examples are:

  • Alpha-1 antitrypsin deficiency (A1AD)
  • Primary Immunodeficiency (PI)
  • Chronic Inflammatory Demyelinating Polyneuropathy (CIDP)
  • Guillain-Barré syndrome (GBS)
  • Hemophilia
  • Rabies
  • Hepatitis B
  • Kawasaki disease

The blockbuster product from the plasma fractionation is immunoglobulin (IVIG or SCIG). immunoglobulin is a life-saving product for primary immunodeficiency patients. Immunoglobulin is also thought to be a panacea for all kinds of neurological diseases (CIDP, GBS, Myasthenia Gravis, multifocal motor neuropathy) that some of which have no other efficacy treatments. 

Many of these diseases treated with plasma-derived products are orphan diseases or ultra-orphan diseases.

Theoretically, plasma-derived products have a risk of carrying bloodborne pathogens (viruses and other pathogens). However, these pathogens are destroyed or filtered out during the manufacturing process. The actual plasma-derived products are very safe - at least in the United States. 

For clinical trials with plasma-derived products, the following points are noted: 

  • Similar to the oncology drugs, the plasma-derived products can not be tested in healthy volunteers. Even for the first-in-human trial, the plasma-derived products will need to be tested directly in the patients.  
  • The study procedure will always need to include the virus tests at screening and possibly the following up visits. 
  • Always include the immunogenicity assessment (because the plasma-derived products are large protein therapies)
  • The design and analyses of clinical trials are the same as other drugs or biological products. For ultra-rare diseases, the single-arm design may be used as the pivotal study and the sample size can be very small. See FDA Approves First Ever Treatment for Plasminogen Deficiency Type 1 based on a single-arm study with 15 adult and pediatric patients with plasminogen deficiency type 1.
  • For pharmacokinetic analysis, the pre-dose drug concentration is not zero since there are endogenous compounds (i.e., enzymes or antibodies that are generated by the patients). 

Useful Links: